Deep Plane Facelift Glossary
This glossary defines, in plain language, the terms a surgeon uses when describing a deep plane facelift: the SMAS layer, the platysma, the retaining ligaments, the deep plane itself and the words of the consultation that follow them, many linked to the page that explains them further. It defines and does not advise, and we hold no study of our own, so no definition here carries a rate or a promise. What DEEPPLANE™ holds as data: 5 440 published before-and-after pairs from 760 surgeons in 58 countries, 30 of them photographed twelve months or more after surgery.
Konzultáció kéréseGyors válasz
What medical terms should I know before a deep plane facelift?
Key terms include SMAS (the muscle-and-fascia layer lifted in surgery), platysma (neck muscle tightened during the procedure), retaining ligaments (anchors released for natural repositioning), and rhytidectomy (the clinical name for facelift). Knowing these 40+ terms helps you decode surgeon notes and ask informed questions.
Forrás: DEEPPLANE™ ·

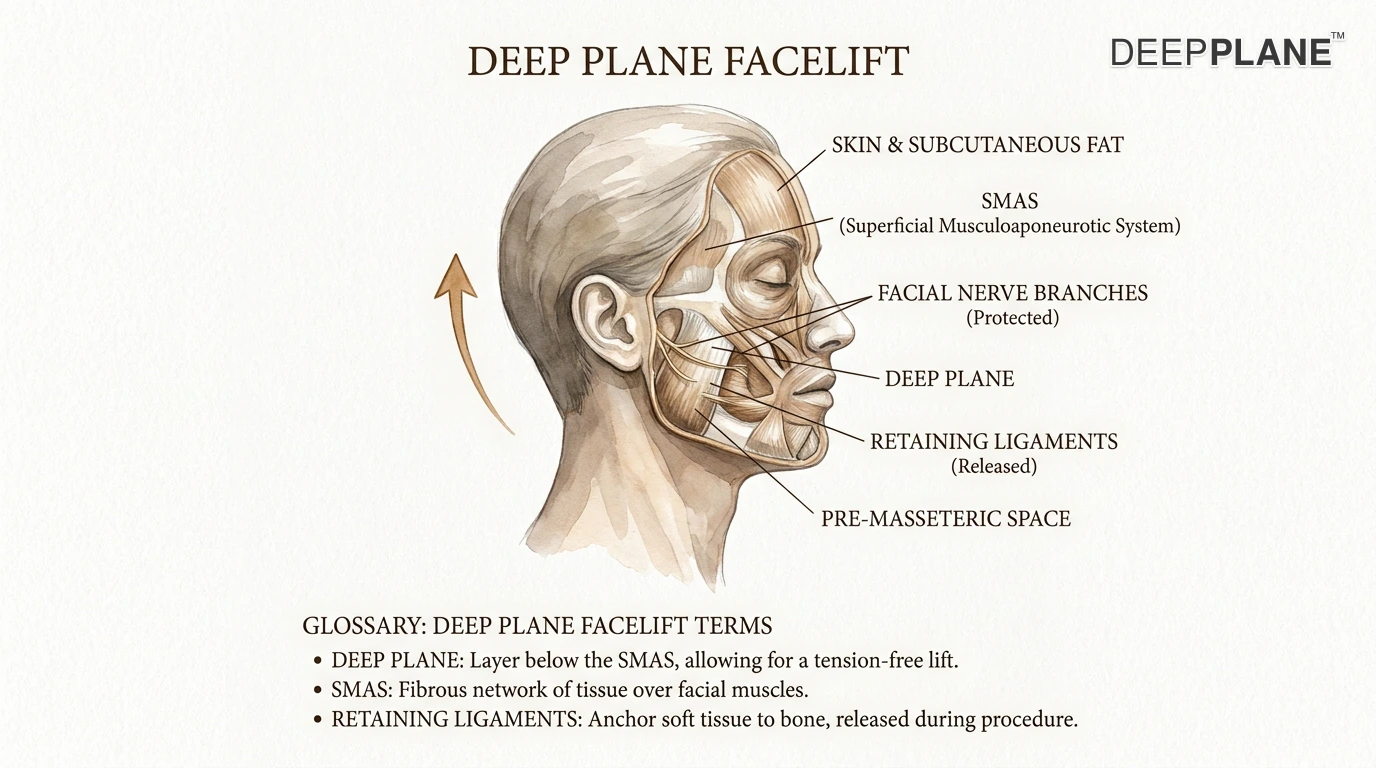
Labeled facial anatomy diagram — reference guide for the surgical structures mentioned throughout this glossary.
Free · No obligation
9
- 9D Facelift
- A marketing term used by some clinics, mainly in China and other parts of Asia, for multi-vector deep plane facelift variants — not a distinct, peer-reviewed surgical technique with standardized anatomy. The number refers to the marketed count of lift directions/vectors rather than a recognized medical classification. Evaluate a surgeon's board certification and documented outcomes rather than branded terminology like this.
A
- Anesthesia (General)
- A medically induced state of complete unconsciousness used during surgery. Deep plane facelifts are most often performed under general anesthesia, administered and monitored by a board-certified anesthesiologist throughout the procedure.
- Anesthesia (Local)
- Medication injected into a specific region to numb sensation while the patient remains fully awake. Occasionally used for minor facial procedures or combined with IV sedation (twilight anesthesia) for select facelift candidates.
- Anesthesia (Tumescent)
- A technique in which large volumes of dilute local anesthetic (lidocaine) combined with epinephrine are infused into the surgical field before dissection. It reduces bleeding, pain, and the need for general anesthetic in some procedures.
- Anesthesia (Twilight)
- Intravenous sedation that places the patient in a deeply relaxed, semi-conscious state combined with local anesthetic. Patients breathe independently. Some surgeons offer twilight anesthesia for mini facelifts.
- Autologous Fat Transfer
- A procedure in which fat is harvested from one area of the patient's own body (commonly the abdomen or thighs), processed, and injected into the face to restore lost volume. Commonly combined with a deep plane facelift to address hollow cheeks or temples.Learn more →
B
- Blepharoplasty
- Eyelid surgery that removes or redistributes excess skin, muscle, and fat from the upper eyelids, lower eyelids, or both. Frequently performed alongside a deep plane facelift for comprehensive facial rejuvenation.
- Brow Lift (Forehead Lift)
- A surgical procedure that elevates the brows and smooths forehead wrinkles. Can be performed endoscopically (3–5 small scalp incisions) or via a coronal incision. Often combined with a deep plane facelift to address upper-face aging.Learn more →
- Buccal Fat Pad
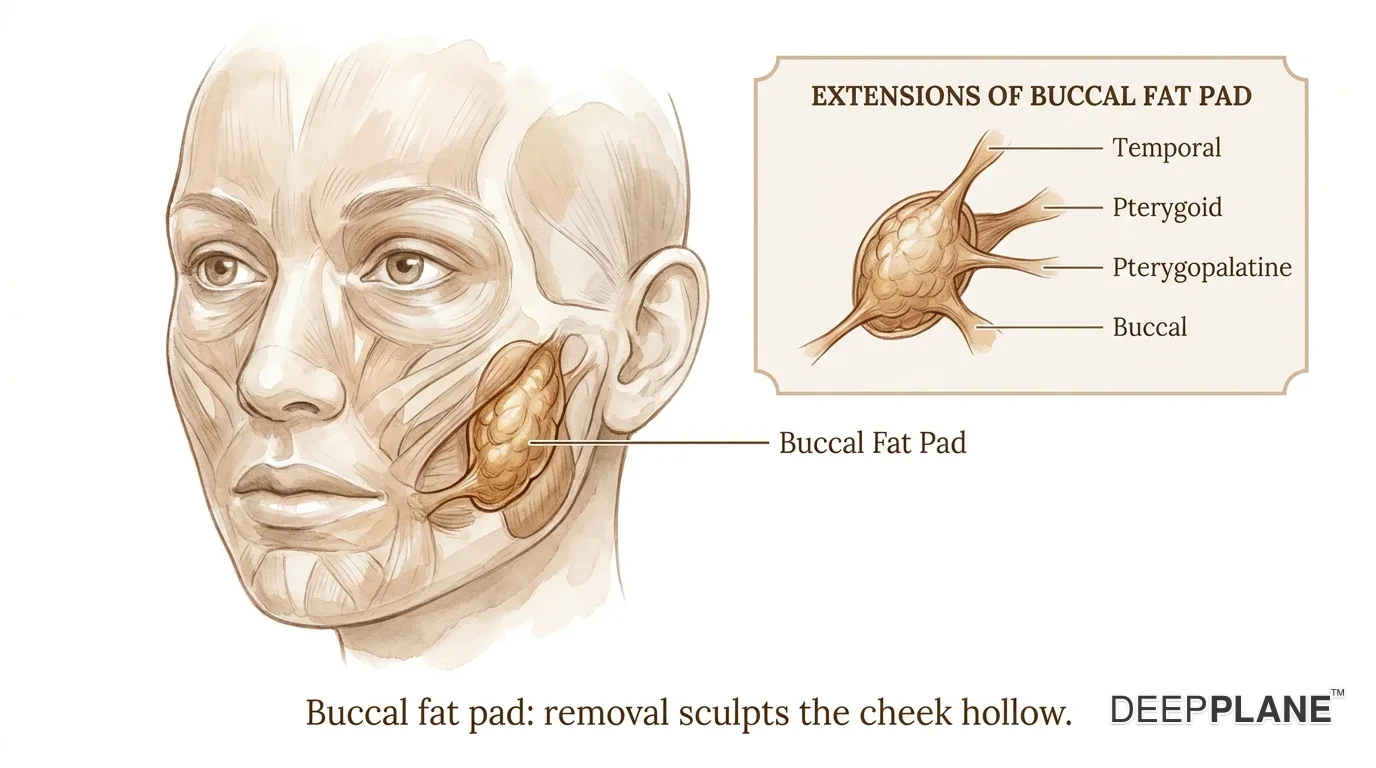
- A lobular fat compartment deep in the cheek hollow, with four extensions (buccal, pterygoid, temporal, pterygopalatine). Surgical removal sculpts the cheek hollow but is irreversible — most facelift surgeons leave it intact and instead address descent at the SMAS level.

C
- Cervicomental Angle
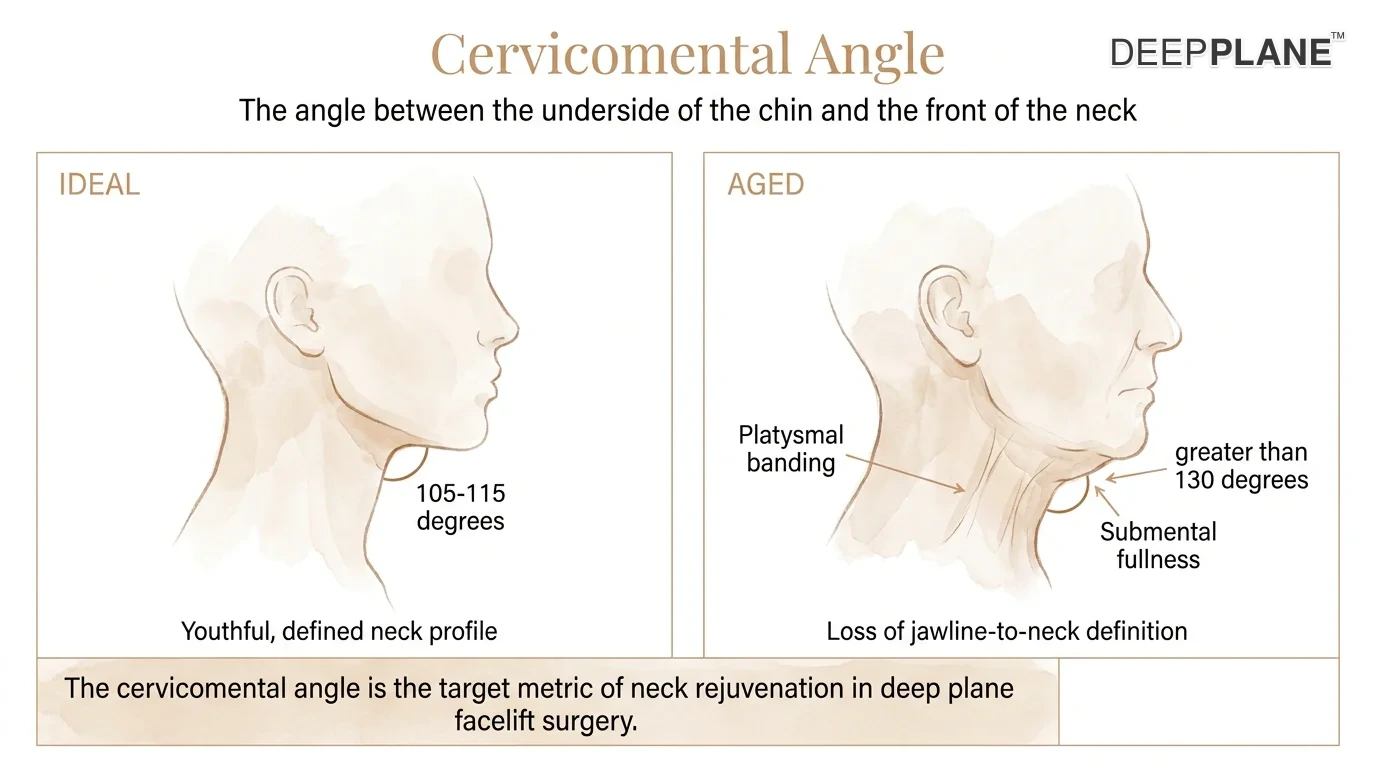
- The angle formed between the underside of the chin and the front of the neck, ideally 90–105 degrees. A well-defined cervicomental angle conveys a youthful neck profile and is a primary goal of combined facelift and neck-lift surgery.Learn more →
- Composite Facelift
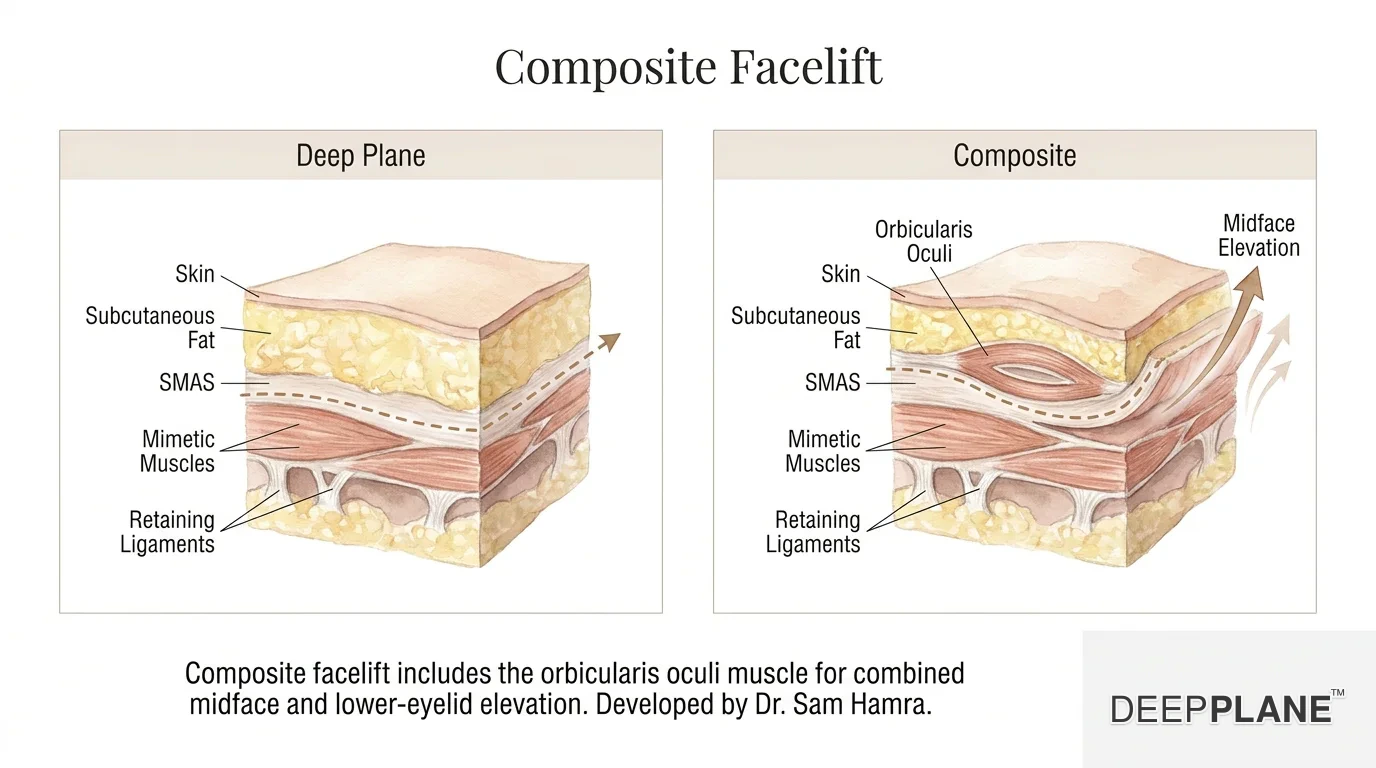
- A variation of the deep plane facelift that also elevates the orbicularis oculi muscle (the muscle encircling the eye) to address lower-eyelid laxity and under-eye bags simultaneously. Developed by Dr. Sam Hamra.Learn more →
- Compression Garment
- A specialised elastic bandage or chin-neck wrap worn after facelift surgery to reduce post-operative swelling, minimise bruising, and help the skin re-adhere to the underlying tissue. Typically worn for 1–2 weeks.


D
- Deep Plane
- The surgical tissue plane that lies immediately beneath the SMAS layer, separating it from the deeper facial muscles and retaining ligaments. Operating in this plane — releasing ligaments and mobilising the composite tissue flap — is the defining feature of a deep plane facelift.Learn more →
- Dissection
- The careful surgical separation of tissue layers. In a deep plane facelift, dissection proceeds beneath the SMAS to release retaining ligaments and lift the entire composite flap — skin, subcutaneous fat, and SMAS — as a single unit.
- Deep Medial Cheek Fat
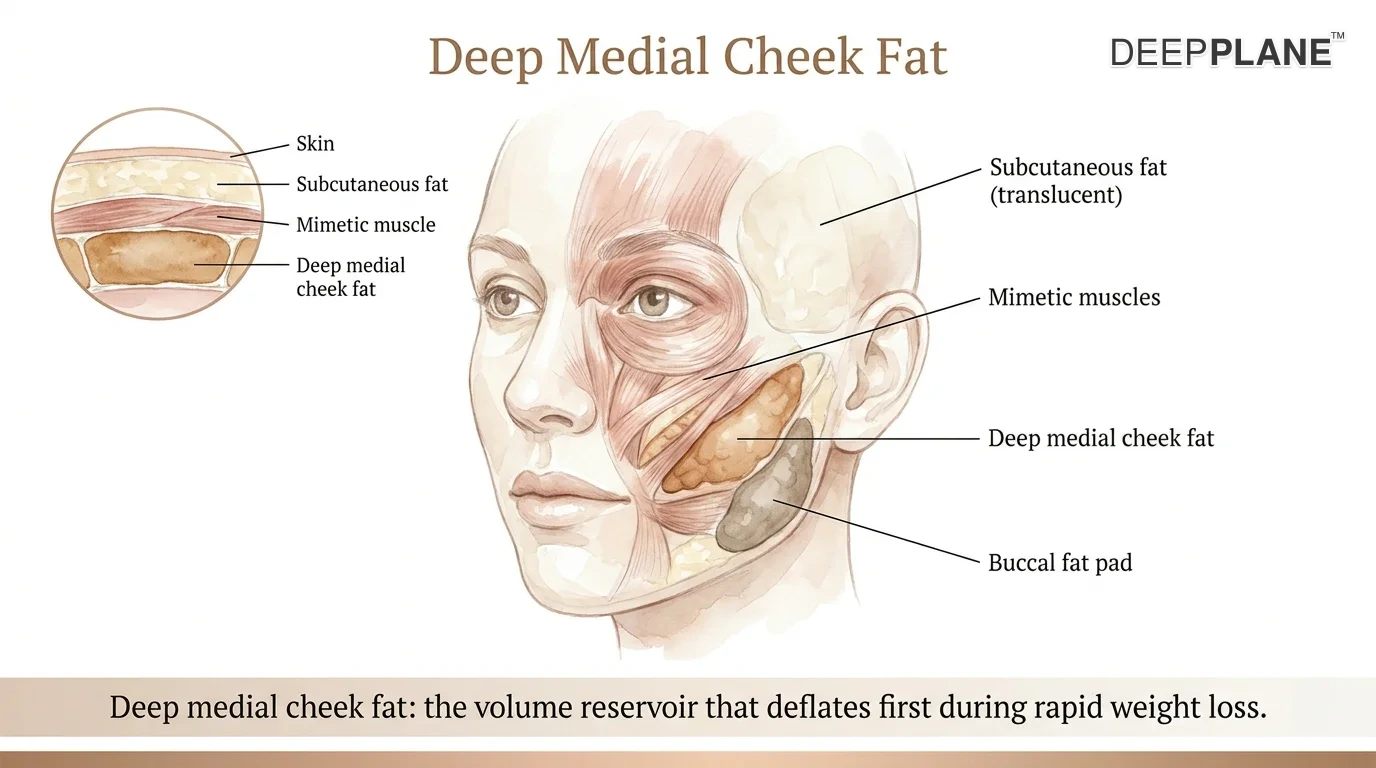
- A discrete fat compartment situated deep to the mimetic muscles, beneath the buccal fat pad. It is the volume reservoir that deflates first during rapid weight loss — a key reason post-GLP-1 patients require fat grafting in addition to a deep plane lift.Learn more →

E
- Edema
- Fluid accumulation in tissue causing swelling. Post-operative edema is normal after a facelift and typically peaks at 48–72 hours. Most visible swelling resolves within 2–3 weeks; residual swelling can persist for 3–6 months.Learn more →
- Extended Deep Plane Facelift
- An extension of the standard deep plane technique in which dissection continues further medially to address the midface, nasolabial folds, and malar fat pad more completely. Provides greater correction of midface descent than a standard deep plane alone.Learn more →
F
- Facial Nerve (CN VII)
- The seventh cranial nerve, which controls all muscles of facial expression. Injury to its branches during facelift surgery can cause temporary or, rarely, permanent weakness. An expert surgeon's thorough knowledge of facial nerve anatomy is the most important safeguard.
- Fat Grafting (Lipofilling)
- Synonymous with autologous fat transfer. Harvested fat cells are purified and micro-injected into areas of facial volume loss. Results can last many years; survival of the transferred fat is typically 50–70%.Learn more →
G
- General Anesthesia
- See Anesthesia (General). Listed separately because it is the most searched form used in deep plane facelift surgery.
H
- Hematoma
- A localised collection of blood outside a blood vessel, forming under the skin after surgery. Hematoma is the most common early complication of facelift surgery (occurring in approximately 1–3% of cases) and usually requires surgical drainage when significant.Learn more →
- Hypertrophic Scarring
- A raised, thickened scar that forms within the boundaries of the original incision. Unlike keloids, hypertrophic scars do not extend beyond the wound edges. Risk is reduced by careful incision placement and post-operative scar care.
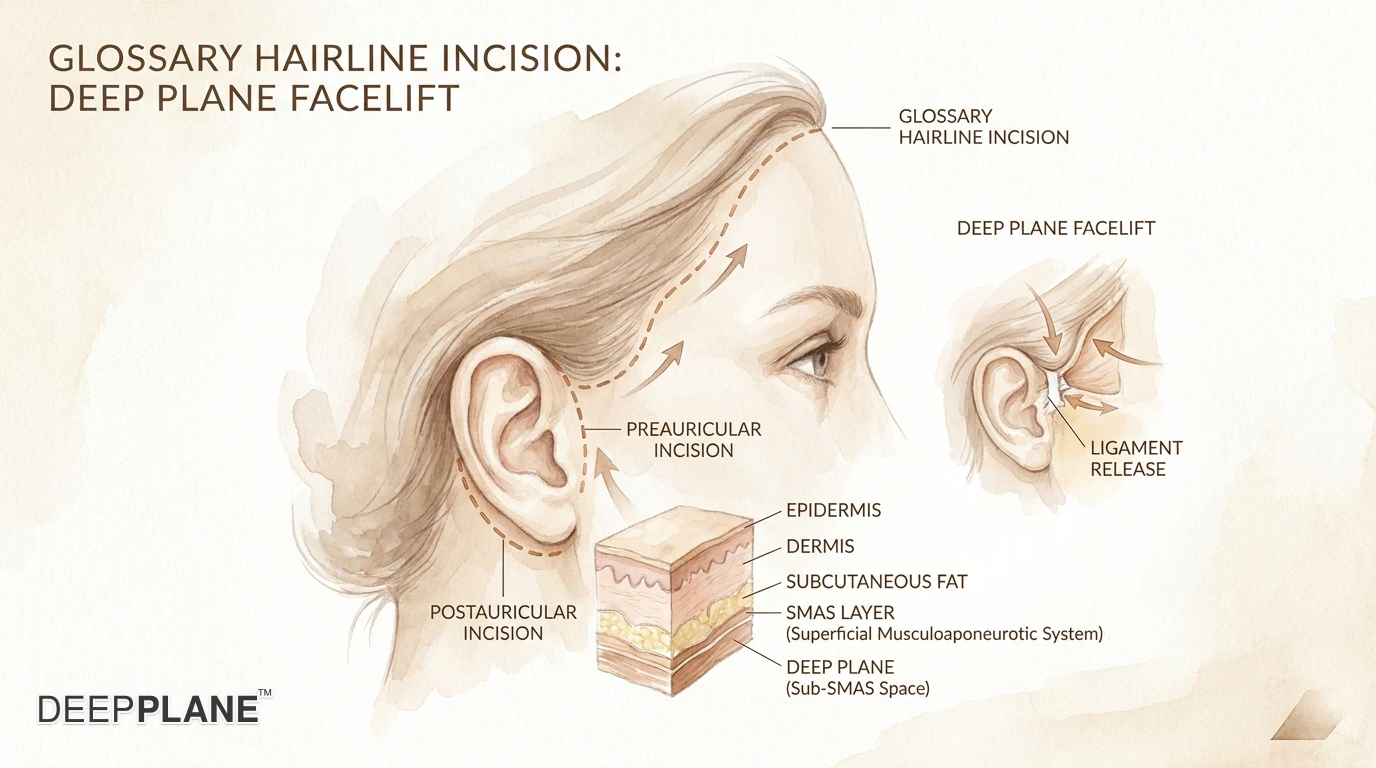
- Hairline-Respecting Incision
- An incision technique that runs along the temporal hairline edge rather than into it, preserving the hairline contour. The classic standard temporal incision can pull the hairline posteriorly; hairline-respecting placement avoids the visible loss of temporal hair density seen after revision-needing facelifts.

I
- Incision
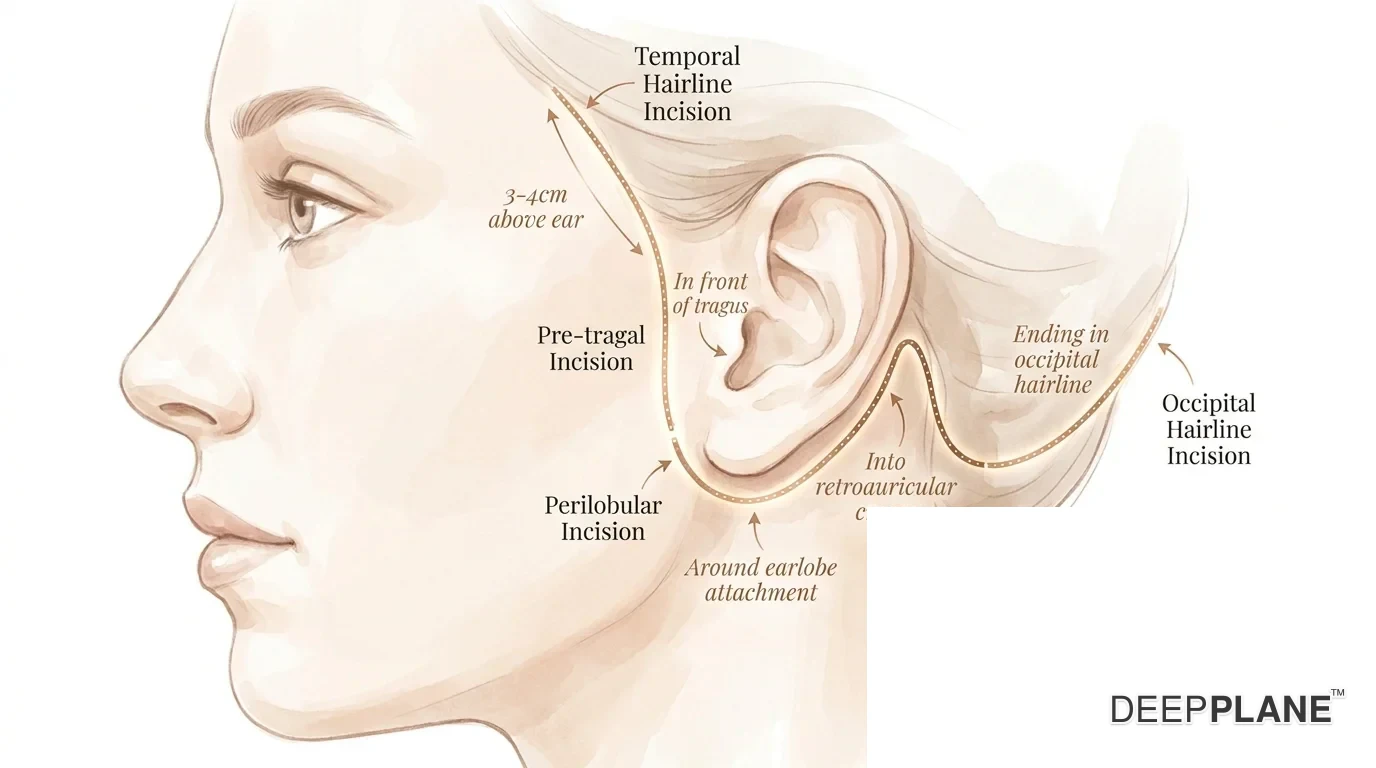
- The surgical cut made at the start of a procedure. Deep plane facelift incisions typically begin in the temple hairline, curve around the front of the ear (pre-auricular), behind the ear lobule, and along the lower posterior hairline — all designed to remain hidden.
J
- Jowls
- Descended soft tissue and fat along the lower jawline, disrupting the sharp angle between the jaw and neck. Jowl correction is one of the primary goals of deep plane facelift surgery, achieved by repositioning the cheek and midface tissues upward.Learn more →
K
- Keloid
- An overgrowth of scar tissue that extends beyond the borders of the original wound. More common in patients with darker skin tones. Surgeons screen for personal or family history of keloids before proceeding with elective surgery.
L
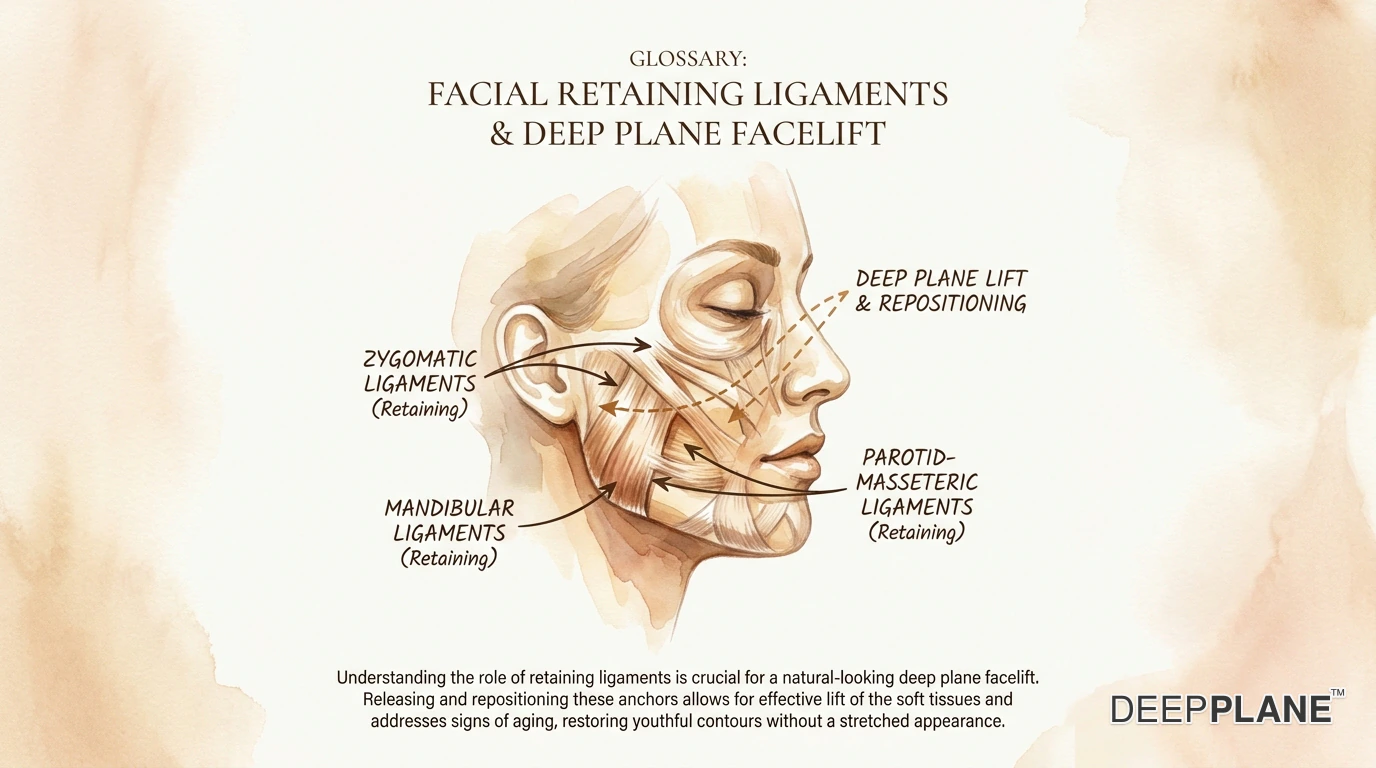
- Ligament Release
- The deliberate surgical division of retaining ligaments (zygomatic, masseteric, mandibular) that tether the overlying soft tissue to the underlying bone. Releasing these ligaments is the key step that allows the deep plane composite flap to be elevated and repositioned.
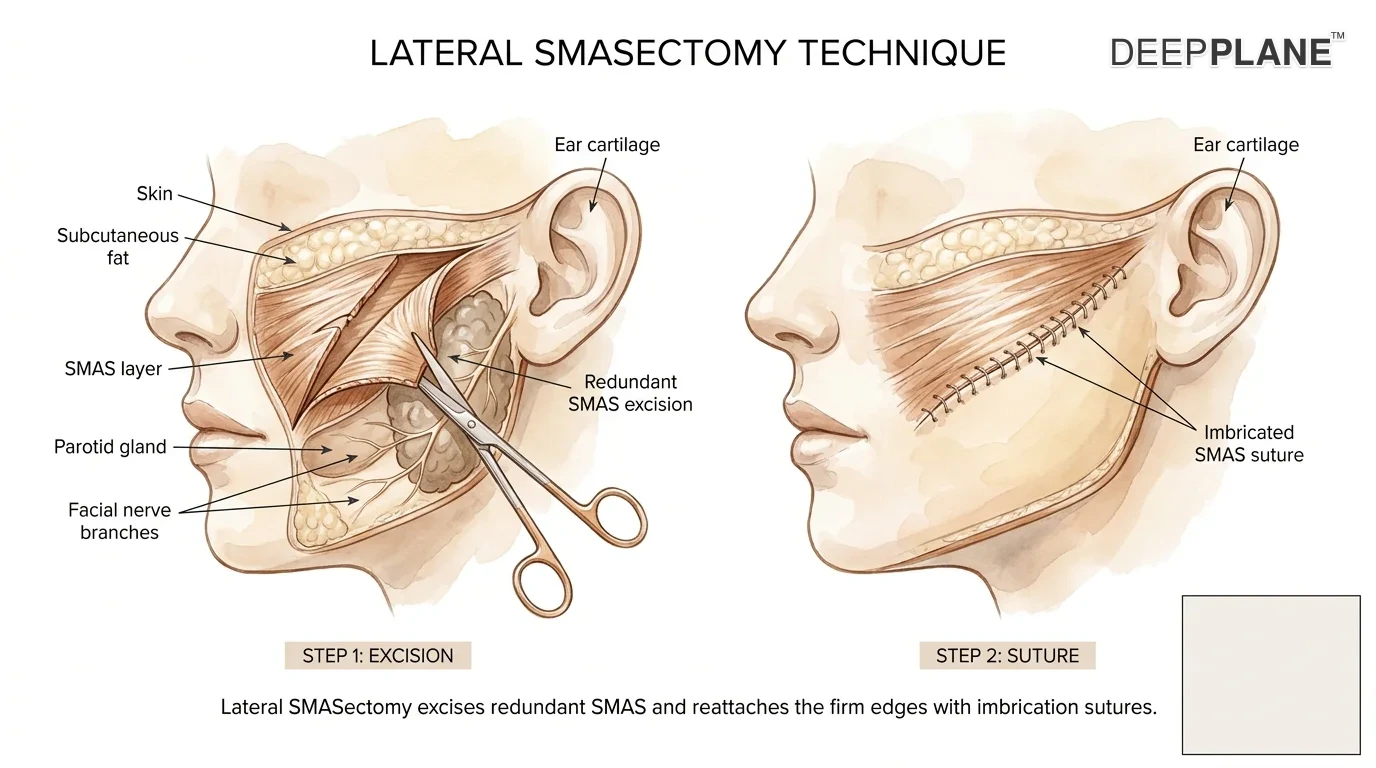
- Lateral SMASectomy
- A SMAS-manipulation technique that excises a precise wedge of redundant SMAS in front of the ear and sutures the cut edges together (imbrication closure). It tightens the lateral face without entering the deep plane — middle-ground between plication and a full deep plane dissection.
- Laxity
- Looseness of tissue. Skin laxity is the slack in the skin itself; deeper laxity is the descent of the SMAS, the retaining ligaments and the fat compartments beneath it. The distinction matters because a skin-only operation can only address the first, which is why a face with mostly deep laxity looks pulled rather than lifted after one.

M
- MACS Lift (Minimal Access Cranial Suspension)
- A short-scar facelift technique that uses purse-string sutures placed through minimal incisions to gather and suspend facial tissue. Less extensive than a full deep plane facelift; suited to mild-to-moderate facial aging.
- Marionette Lines
- Vertical creases that descend from the corners of the mouth toward the jawline, creating a downturned or sad appearance. Named after marionette puppets. Deep plane facelift repositions the underlying tissue to soften these lines.Learn more →
- Mini Facelift
- A less extensive facelift using shorter incisions and more limited dissection, typically addressing mild lower-face laxity. Recovery is shorter (1–2 weeks) but results are less dramatic than a full deep plane facelift; how long they last has not been measured in a series we can cite.Learn more →
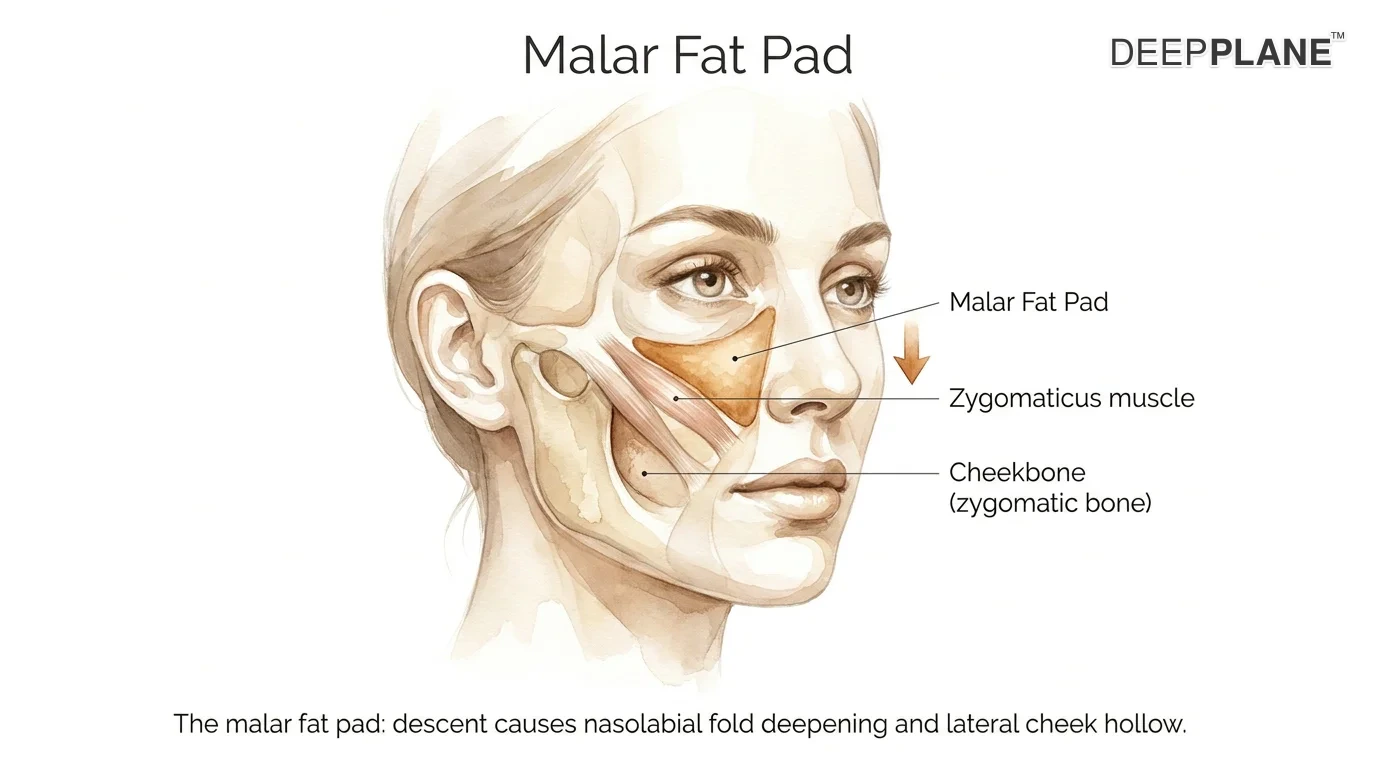
- Malar Fat Pad
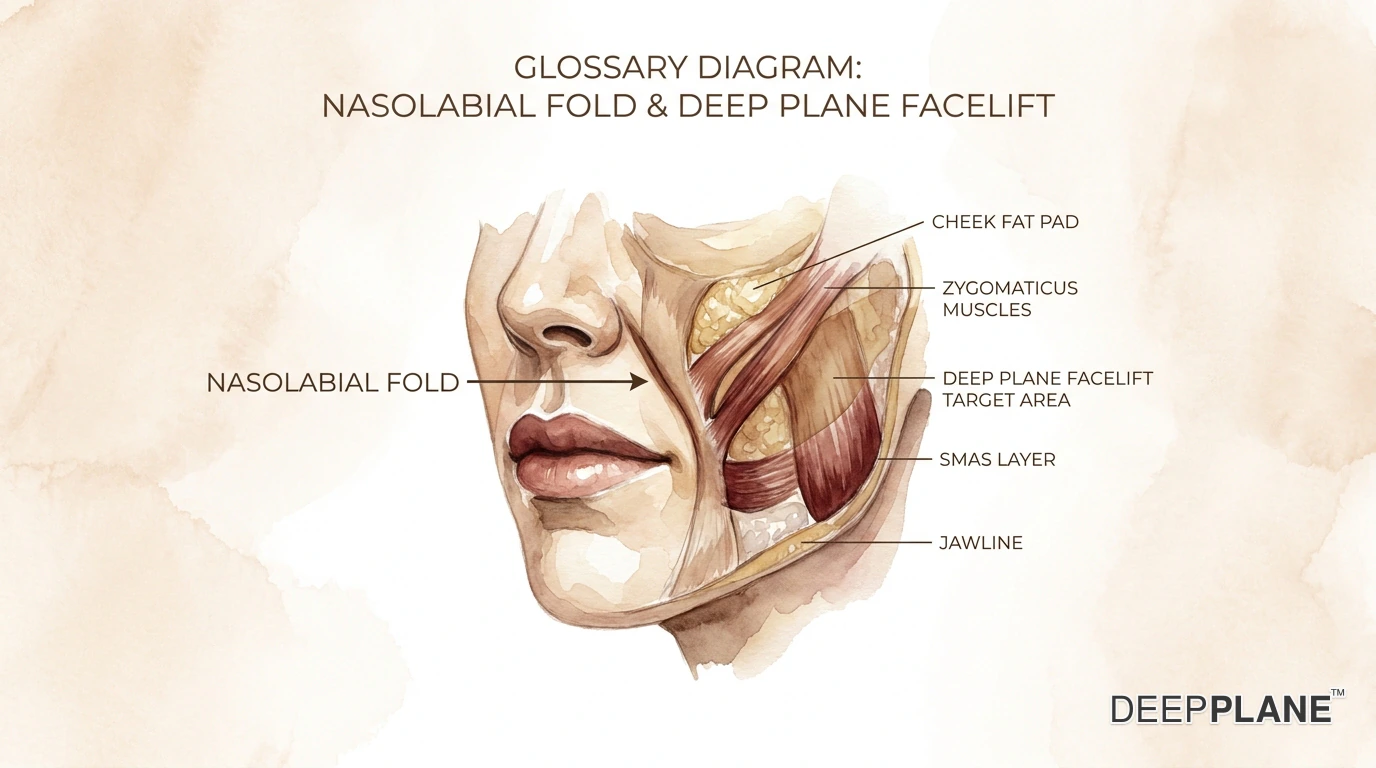
- A triangular subcutaneous fat compartment overlying the zygomaticus muscle and cheekbone. Its descent with age is what causes nasolabial fold deepening and lateral cheek hollow — repositioning it superiorly is one of the defining goals of the extended deep plane facelift.Learn more →
- Mid-Facelift
- A targeted facelift addressing only the midface — restoring malar volume vertically through the lower lid via a conjunctival or temporal incision. Limited to the malar and infraorbital region; does not address jowls or neck laxity, so rarely chosen as a stand-alone procedure today.Learn more →
- Midface
- The region between the lower eyelid and the corner of the mouth, containing the cheekbone, the malar fat pad and the nasolabial fold. It is the area a deep plane dissection reaches once the zygomatic and masseteric retaining ligaments are released, and the reason the technique changes cheek position rather than only jawline tightness.Learn more →


N
- Nasolabial Fold
- The crease running from the side of each nostril to the corner of the mouth, sometimes called the smile line or laugh line. Deepening of these folds is a hallmark of midface descent. The extended deep plane technique directly addresses them by lifting the malar fat pad.Learn more →
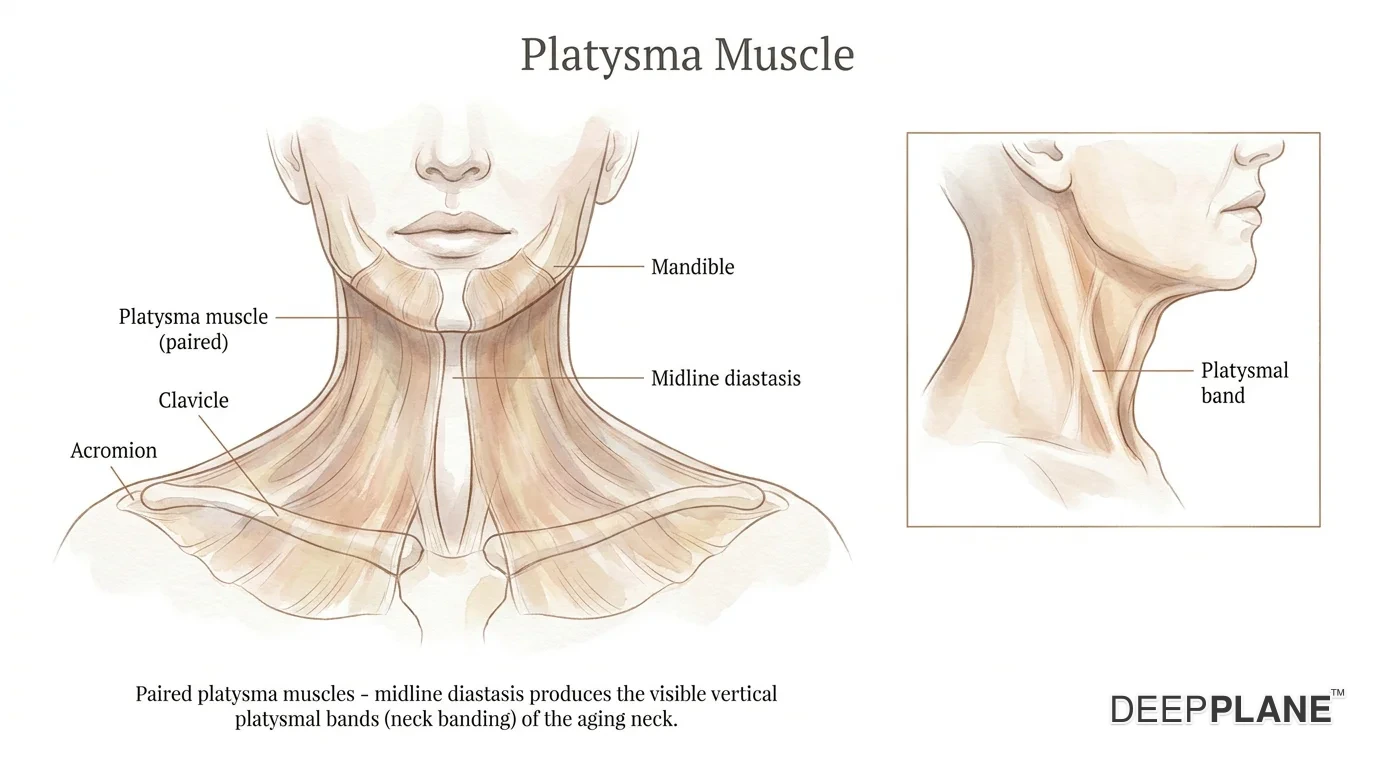
- Neck Banding (Platysmal Bands)
- Vertical cords that appear on the neck as the platysma muscle separates with age. Addressed during neck lift surgery by suturing the muscle edges together (platysmaplasty) at the midline, restoring a smooth contour.Learn more →
- Nerve Damage
- Unintended injury to sensory or motor nerves during surgery. Temporary numbness or tingling around the ear is common after facelift and usually resolves within weeks to months. Permanent motor nerve injury is rare (<1%) in experienced hands.

P
- Platysma
- A broad, thin muscle that extends from the upper chest and shoulder to the lower jaw and chin. Laxity of this muscle creates neck banding and the 'turkey neck' appearance. Tightening the platysma via platysmaplasty is a standard component of a deep plane facelift with neck lift.
- Ponytail Facelift
- A minimally invasive technique that uses small hairline incisions to achieve a subtle upward lift, mimicking the look of pulling hair into a tight ponytail. Results are less comprehensive and durable than a full deep plane facelift.Learn more →
- Pre-auricular Incision
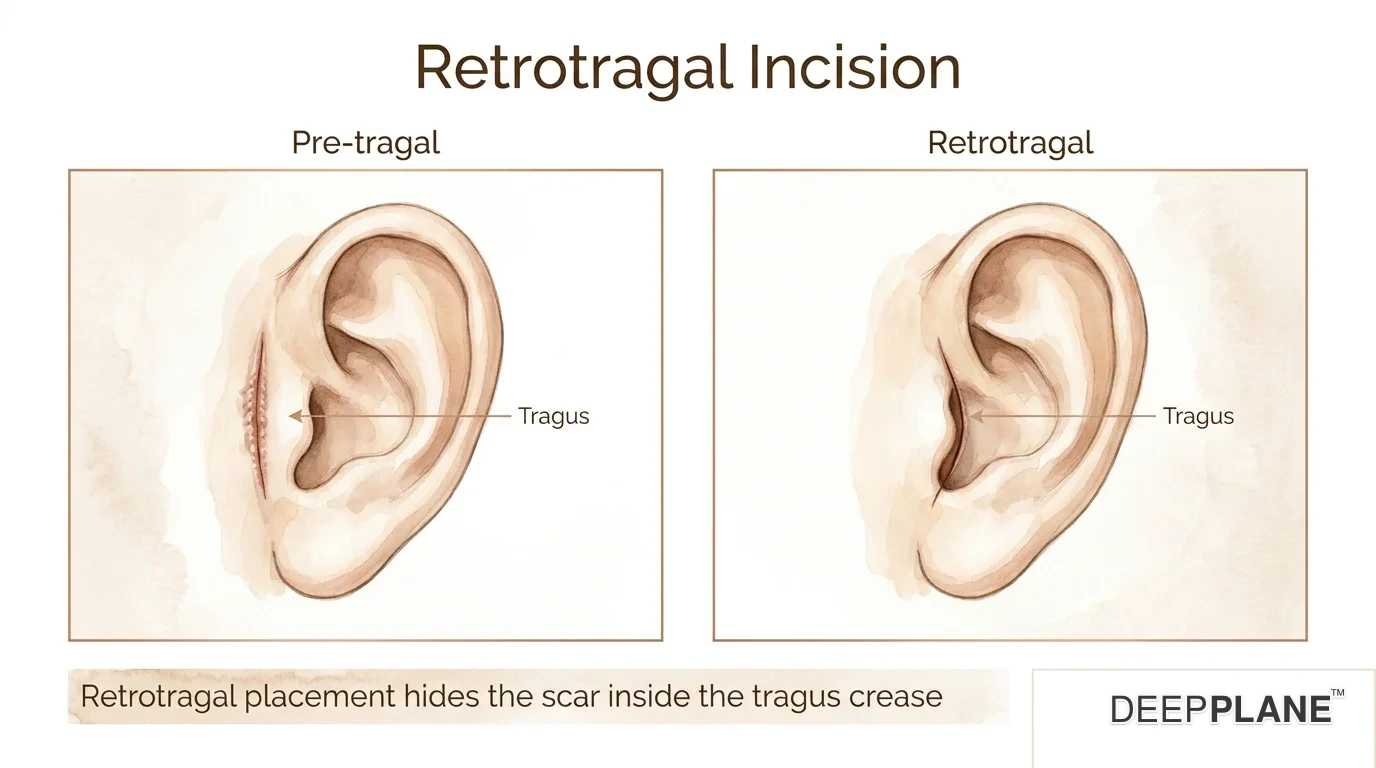
- The standard facelift incision running in front of the ear (from the temporal hairline, down to or inside the tragus, around the earlobe, and into the retroauricular crease and occipital hairline). Variants like the retrotragal placement hide the scar inside the tragus crease.
- Pixie Ear
- An earlobe pulled downward and stretched into the cheek, so that it no longer hangs free. It is a sign of tension carried by the skin at the earlobe rather than by the deeper layer, and it is one of the results most commonly asked about in revision consultations.Learn more →
- Platysmaplasty
- Surgical tightening of the platysma, the broad sheet of muscle across the front of the neck. In an anterior platysmaplasty the two edges of the muscle are joined in the midline through a small incision under the chin; a lateral platysmaplasty tightens the muscle from the sides. It is a neck operation, and it is often performed in the same sitting as a facelift rather than instead of one.Learn more →
- Ptosis
- Drooping. The word is used for several different structures, so it is only meaningful with the structure named: brow ptosis is a descended eyebrow, eyelid ptosis is a drooping upper lid margin, and malar ptosis is the descent of the cheek fat pad. A facelift addresses the third and not the first two.


R
- Retaining Ligaments
- Dense fibrous structures that anchor the facial soft tissues to the underlying bone and muscle fascia. The key retaining ligaments in facelift surgery are the zygomatic, masseteric, and mandibular ligaments. Releasing them is the defining step of the deep plane technique.
- Revision Facelift
- A facelift that re-enters the dissection field of a previous one — the cervicofacial flap and SMAS/platysma. Any prior facelift technique counts (SMAS, skin-only, deep plane, MACS), as does an isolated neck lift; prior eyelid surgery, brow lift or fat grafting does not. It covers both correcting an unsatisfactory result and lifting again after years of natural ageing, and is technically more demanding than a primary because of scarring, altered tissue planes and obscured nerve landmarks.
- Rhytidectomy
- The medical (Greek-derived) term for a facelift. Rhytis = wrinkle, ektomia = excision. The term encompasses all facelift techniques, from mini facelifts to the extended deep plane. 'Facelift' and 'rhytidectomy' are used interchangeably in medical literature.
- Retrotragal Incision
- An incision placement that runs INSIDE the tragus (the ear cartilage flap) rather than in front of it. Hides the resulting scar inside the natural tragal crease — the preferred placement for female facelift patients because the pre-tragal scar can be visible with hair pulled back.


S
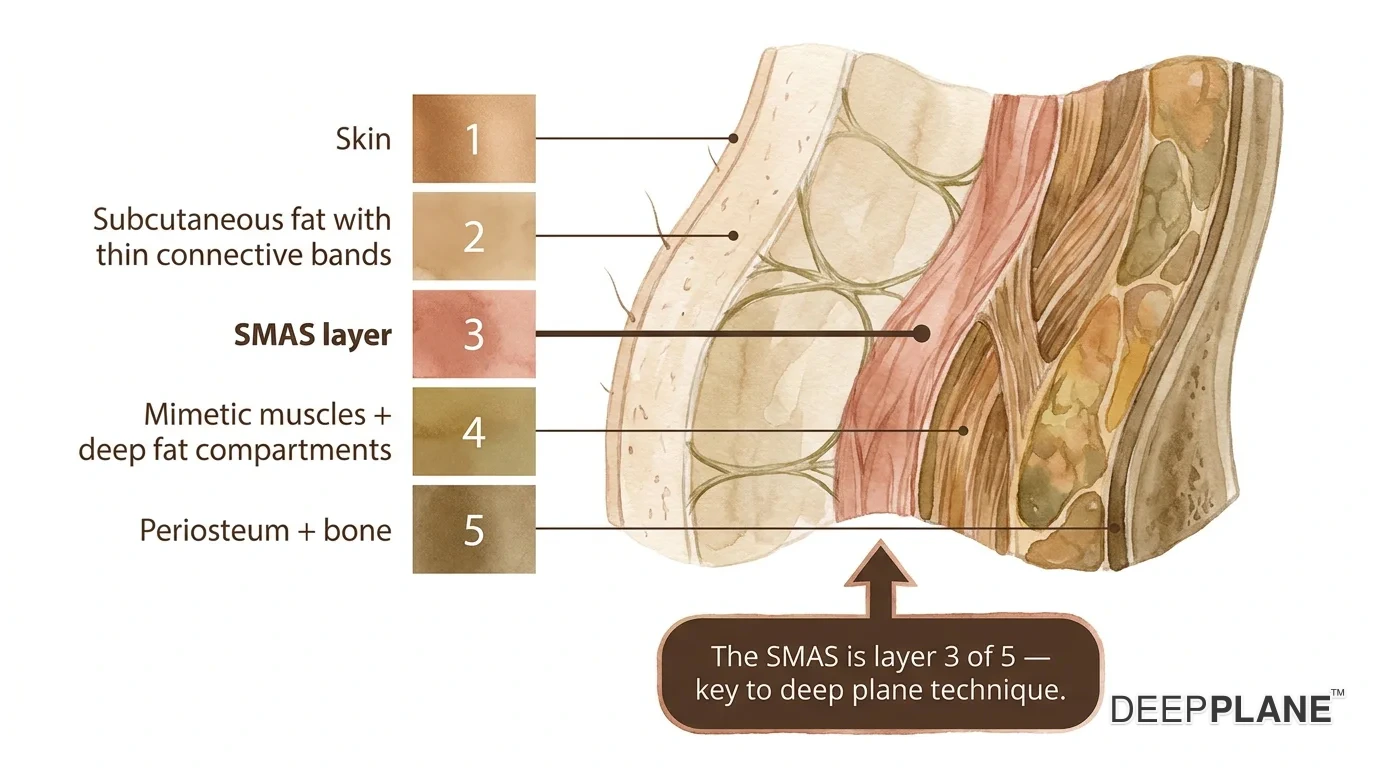
- SMAS (Superficial Musculoaponeurotic System)
- A fibromuscular layer of tissue lying just beneath the facial subcutaneous fat. It connects the superficial facial muscles to the overlying skin. Manipulating the SMAS — whether by plication, imbrication, or the deep plane approach — is fundamental to achieving a natural facelift result.Learn more →
- Subperiosteal Facelift
- A facelift technique in which dissection occurs at the deepest plane, directly beneath the periosteum (the covering of the facial bones). Provides maximal midface elevation but carries greater risks and a longer recovery than the deep plane approach.
- Superficial Plane (Sub-SMAS Plane)
- The tissue plane immediately above the SMAS layer. Traditional facelift techniques (skin-only or SMASectomy) operate in this superficial plane, producing shorter-lasting results and a higher risk of an artificial, 'pulled' appearance compared to deep plane techniques.
- Skin-Only Facelift
- A facelift in which the skin is lifted and trimmed without any work on the SMAS beneath it. It is the oldest form of the operation. Because all of the tension is carried by the skin, the result tends to be short-lived and can produce a tightened look at the edges of the face while the midface stays where it was.
- Submental
- Under the chin. A submental incision is the small opening made there to reach the platysma and the fat directly beneath the jaw, and submental fullness is the term for the fat and muscle laxity that blunts the angle between chin and neck.Learn more →

T
- Thread Lift
- A non-surgical or minimally invasive procedure in which barbed dissolvable sutures are inserted under the skin to provide a temporary lifting effect. The effect is temporary: in a 2025 review of absorbable threads the longest follow-up was 2 years, and long-term efficacy data are lacking (Riopelle 2025, PMID 39662017). Suitable for mild laxity only.Learn more →
- Tissue Glue (Fibrin Sealant)
- A biological adhesive applied to the surgical field to reduce post-operative hematoma and seroma formation. Some surgeons use fibrin sealant at the end of a deep plane facelift to improve tissue adhesion and shorten bruising duration.
- Tri-Vector Deep Plane
- An advanced deep plane variation that repositions the facial composite flap in three independent vectors simultaneously — vertical for the jowl/neck, oblique for the midface, and lateral for the temporal region — achieving more nuanced, natural correction than a single-vector lift.Learn more →
- Temporal Hairline
- The edge of the hair above and in front of the ear. Facelift incisions either run into it or along it, and the choice shows: an incision carried into the hair can move the hairline backwards and thin the hair in front of the ear, which is why hairline-respecting placement exists.
V
- Vertical Facelift
- A facelift philosophy that lifts tissue vertically (upward) rather than laterally (toward the ear). Vertical vector lifting more closely reverses the direction of gravitational aging and reduces the risk of an unnatural, laterally stretched appearance.
Z
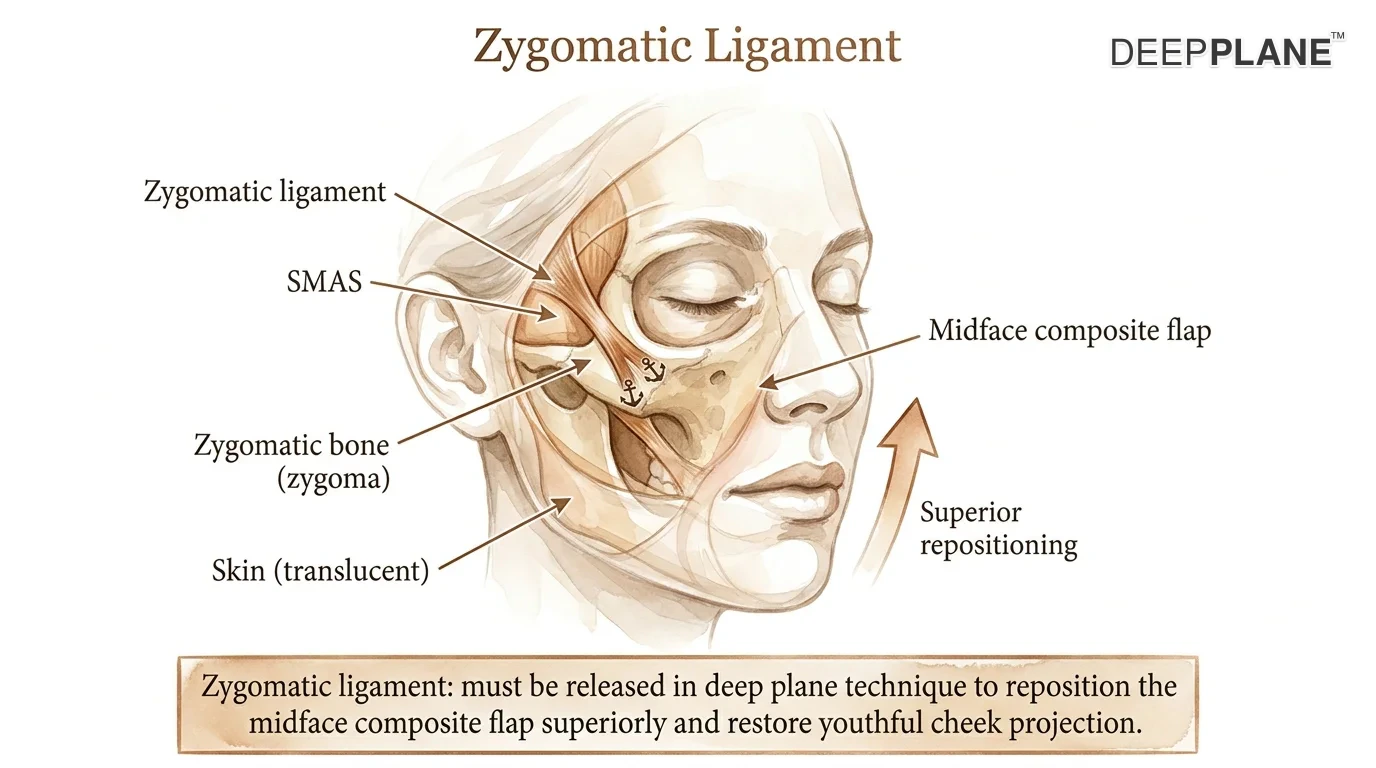
- Zygomatic Ligament
- A retaining ligament that anchors the soft tissue over the cheekbone to the underlying zygoma. Releasing the zygomatic ligament is an essential step in the deep plane technique, enabling the midface composite flap to be repositioned superiorly to restore youthful cheek projection.

Board Certifications, Societies & Fellow Titles
Many surgeon profiles list credentials like "ABFPRS", "EBOPRAS", or "FACS". Below is the canonical catalog used across DEEPPLANE™ — every credential shown on a profile resolves to one of these entries. Each maps to a country / regulator so you can verify what a code actually means.
Board Certifications (79)
National boards that certify surgeons after passing examinations and meeting practice requirements. The strongest credential signal — board certification typically requires several years of accredited training, written + oral examinations, and ongoing recertification.
- ABPS— USA
- American Board of Plastic Surgery
- ABFPRS— USA
- American Board of Facial Plastic and Reconstructive Surgery
- ABOHNS— USA
- American Board of Otolaryngology – Head and Neck Surgery
- ABFCS— USA
- American Board of Facial Cosmetic Surgery
- ABCS— USA
- American Board of Cosmetic Surgery
- ABMS— USA
- American Board of Medical Specialties
- ABS— USA
- American Board of Surgery
- ABD— USA
- American Board of Dermatology
- ABO— USA
- American Board of Ophthalmology
- CMCPER— Mexico
- Mexican Council of Plastic, Aesthetic and Reconstructive Surgery
- CMOCCC— Mexico
- Mexican Council of Otolaryngology and Head and Neck Surgery
- EBPS— Egypt
- Egyptian Board of Plastic Surgery
- DBO-HNO— Germany
- German Board of Otolaryngology (Hals-, Nasen- und Ohrenheilkunde)
- PBPS— Philippines
- Philippine Board of Plastic Surgery
- RCPSC— Canada
- Royal College of Physicians and Surgeons of Canada
- FRCS-Plast— UK
- Fellow of the Royal College of Surgeons (Plastic Surgery)
- GMC-Specialist— UK
- GMC Specialist Register (Plastic Surgery)
- RCSEd— UK
- Royal College of Surgeons of Edinburgh
- RCS-England— UK
- Royal College of Surgeons of England
- RCSI— Ireland
- Royal College of Surgeons in Ireland
- EBOPRAS— Europe
- European Board of Plastic, Reconstructive and Aesthetic Surgery
- EBFPRS— Europe
- European Board of Facial Plastic and Reconstructive Surgery
- EBCFPRS— Europe
- European Board for Certification in Facial Plastic and Reconstructive Surgery
- IBCFPRS— International
- International Board for Certification in Facial Plastic and Reconstructive Surgery
- EBO— Europe
- European Board of Ophthalmology
- OEGPAERC— Austria
- Austrian Society of Plastic, Aesthetic and Reconstructive Surgery
- SGPRAC— Switzerland
- Swiss Society of Plastic, Reconstructive and Aesthetic Surgery
- CNOM-CP— France
- Conseil National de l'Ordre des Médecins – Chirurgie Plastique (France)
- SICPRE— Italy
- Italian Society of Plastic, Reconstructive and Aesthetic Surgery
- SPCPRE— Portugal
- Portuguese Society of Plastic, Reconstructive and Aesthetic Surgery
- HSPRAS— Greece
- Hellenic Society of Plastic, Reconstructive and Aesthetic Surgery
- NSPRAS— Nordics
- Nordic Society for Plastic Surgery
- NVPC— Netherlands
- Dutch Society for Plastic Surgery
- TPRECD— Turkey
- Turkish Board of Plastic, Reconstructive and Aesthetic Surgery
- SBCP— Brazil
- Brazilian Society of Plastic Surgery
- FILACP— LATAM
- Ibero-Latin American Federation of Plastic Surgery
- AMCPER— Mexico
- Mexican Association of Plastic, Aesthetic and Reconstructive Surgery
- SCCP— Colombia
- Colombian Society of Plastic Surgery
- SCHCPRE— Chile
- Chilean Society of Plastic, Reconstructive and Aesthetic Surgery
- PASMENA— MENA
- Plastic and Aesthetic Surgery MENA Council
- ESPRS— Egypt
- Egyptian Society of Plastic and Reconstructive Surgery
- SSPS— Saudi Arabia
- Saudi Society of Plastic Surgery
- JSAPS— Japan
- Japan Society of Aesthetic Plastic Surgery
- JSPRS— Japan
- Japan Society of Plastic and Reconstructive Surgery
- KSPRS— South Korea
- Korean Society of Plastic and Reconstructive Surgeons
- KAPS— South Korea
- Korean Association of Plastic Surgeons
- APSI— India
- Association of Plastic Surgeons of India
- ASPS-AU— Australia
- Australian Society of Plastic Surgeons
- APRSSA— South Africa
- Association of Plastic and Reconstructive Surgeons of Southern Africa
- ANZBCPS— Australia / NZ
- Australia and New Zealand Board of Cosmetic Plastic Surgery
- ABOMS— USA
- American Board of Oral and Maxillofacial Surgery
- CPSP— Pakistan
- College of Physicians and Surgeons of Pakistan
- AOBOHNS— USA
- American Osteopathic Board of Otolaryngology – Head and Neck Surgery
- EBOMS— Europe
- European Board of Oral and Maxillofacial Surgery
- ABIM— USA
- American Board of Internal Medicine
- CMORL— Mexico
- Consejo Mexicano de Otorrinolaringología
- ABORL-CCF— Brazil
- Associação Brasileira de Otorrinolaringologia e Cirurgia Cérvico-Facial
- SBCCP— Brazil
- Sociedade Brasileira de Cirurgia de Cabeça e Pescoço
- Facharzt— Germany
- Facharzt für Plastische und Ästhetische Chirurgie
- FMH— Switzerland
- FMH Swiss Medical Association
- IBCS— International
- International Board of Cosmetic Surgery
- TKBB— Turkey
- Turkish Society of Otorhinolaryngology Head and Neck Surgery
- IBMS— Iraq
- Iraqi Board for Medical Specializations
- AOBOO— USA
- American Osteopathic Board of Ophthalmology and Otolaryngology
- EB-ORL-HNS— Europe
- European Board of Otorhinolaryngology — Head and Neck Surgery
- KBPS— South Korea
- Korean Board of Plastic Surgery
- SAB-SG— Singapore
- Specialist Accreditation Board, Ministry of Health, Singapore
- TBPS— Thailand
- Thai Board of Plastic and Reconstructive Surgery
- MCT— Thailand
- Medical Council of Thailand
- DBPS-TH— Thailand
- Diplomate Board of Plastic Surgery (Thailand)
- IBPRAS— Iran
- Iranian Board of Plastic, Reconstructive, and Aesthetic Surgery
- EBDV— Europe
- European Board of Dermatology and Venereology
- CBAM— Canada
- Canadian Board of Aesthetic Medicine
- EBOMFS— Europe
- European Board of Oro-Maxillofacial Surgery
- KBMS— Iraq
- Kurdistan Board of Medical Specialties
- RUSSIAN-MOH— Russia
- Russian Ministry of Health Specialist Certification
- RUSSIAN-BOARD— Russia
- Russian Board of Plastic and Aesthetic Surgery
- ONM-FR— France
- Ordre National des Médecins (France)
- COLOMBIAN-BOARD— Colombia
- Colombian Board of Plastic, Reconstructive & Aesthetic Surgery
Professional Society Memberships (88)
Voluntary associations a surgeon has joined. Membership signals professional engagement but is generally less rigorous than board certification — most societies require a paid annual fee and verification of training, not separate examinations.
- RBSPS— Belgium
- Royal Belgian Society for Plastic Surgery
- SPCP— Peru
- Peruvian Society of Plastic Surgery
- ISAPS— International
- International Society of Aesthetic Plastic Surgery
- LSPRAS— Lebanon
- Lebanese Society of Plastic, Reconstructive and Aesthetic Surgery
- IPRAS— International
- International Confederation for Plastic, Reconstructive and Aesthetic Surgery
- ICOPLAST— International
- International Confederation of Plastic Surgery Societies
- WSPS— International
- World Society of Plastic Surgeons
- ASPS— USA
- American Society of Plastic Surgeons
- ASAPS— USA
- American Society for Aesthetic Plastic Surgery (The Aesthetic Society)
- ACS— USA
- American College of Surgeons
- AAFPRS— USA
- American Academy of Facial Plastic and Reconstructive Surgery
- ASLMS— USA
- American Society for Laser Medicine and Surgery
- ASOPRS— USA
- American Society of Ophthalmic Plastic and Reconstructive Surgery
- AAPS— USA
- American Association of Plastic Surgeons
- PSRC— USA
- Plastic Surgery Research Council
- NESPS— USA
- Northeastern Society of Plastic Surgeons
- RhinoplastySocietyUS— USA
- The Rhinoplasty Society
- AAO— USA
- American Academy of Ophthalmology
- DSPS— USA
- Dallas Society of Plastic Surgeons
- LASPS— USA
- Los Angeles Society of Plastic Surgeons
- CSRS— USA
- California Society of Rhinoplasty Specialists
- BAAPS— UK
- British Association of Aesthetic Plastic Surgeons
- BAPRAS— UK
- British Association of Plastic, Reconstructive and Aesthetic Surgeons
- BAOMS— UK
- British Association of Oral and Maxillofacial Surgeons
- ESPRAS— Europe
- European Society of Plastic, Reconstructive and Aesthetic Surgery
- EASAPS— Europe
- European Association of Societies of Aesthetic Plastic Surgery
- EAFPS— Europe
- European Academy of Facial Plastic Surgery
- VDAEPC— Germany
- Association of German Aesthetic Plastic Surgeons
- DGAEPC— Germany
- German Society of Aesthetic Plastic Surgery
- DGPRAEC— Germany
- German Society of Plastic, Reconstructive and Aesthetic Surgeons
- SOFCEP— France
- French Society of Aesthetic Plastic Surgery
- SOFCPRE— France
- French Society of Plastic, Reconstructive and Aesthetic Surgery
- AICPE— Italy
- Italian Association of Aesthetic Plastic Surgery
- TSPRAS— Turkey
- Turkish Society of Plastic, Reconstructive and Aesthetic Surgery
- TTB— Turkey
- Turkish Medical Association
- OSAPS— Asia-Pacific
- Oriental Society of Aesthetic Plastic Surgery
- SBCP-Mem— Brazil
- Brazilian Society of Plastic Surgery (Member)
- RIPS— Europe
- Rhinoplasty Society of Europe
- KSAPS— South Korea
- Korean Society for Aesthetic Plastic Surgery
- CAFPRS— Canada
- Canadian Academy of Facial Plastic and Reconstructive Surgery
- IBFPRS— International
- International Board for Facial Plastic and Reconstructive Surgery
- AECEP— Spain
- Spanish Association of Aesthetic Plastic Surgery
- IMCAS— International
- International Master Course on Aging Science
- IRRS— International
- International Rhinoplasty Research Society
- SFCPRE— France
- French Facial Plastic Surgery Society
- AACS— USA
- American Academy of Cosmetic Surgery
- SECPRE— Spain
- Spanish Society of Plastic, Reconstructive and Aesthetic Surgery
- SACPER— Argentina
- Argentine Society of Plastic, Reconstructive and Aesthetic Surgery
- PERAPI— Indonesia
- Perhimpunan Dokter Spesialis Bedah Plastik Rekonstruksi dan Estetik Indonesia
- IDI— Indonesia
- Ikatan Dokter Indonesia (Indonesian Medical Association)
- KMA— South Korea
- Korean Medical Association
- KRS— South Korea
- Korean Rhinologic Society
- ASOHNS— Australia / NZ
- Australian Society of Otolaryngology Head and Neck Surgery
- ASAPS-AU— Australia / NZ
- Australasian Society of Aesthetic Plastic Surgeons
- PDS— Philippines
- Philippine Dermatological Society
- PAPRAS— Philippines
- Philippine Association of Plastic, Reconstructive and Aesthetic Surgeons
- HNCS— International
- Head and Neck Cancer Society
- WOFAPS— International
- World Federation of Associations of Pediatric Surgeons
- AOCMF— International
- AO Foundation Craniomaxillofacial
- CNOM— France
- Conseil National de l'Ordre des Médecins
- CMC— Colombia
- Colegio Médico Colombiano
- SMRRP— Mexico
- Sociedad Mexicana de Rinología y Cirugía Plástica Facial
- KCCS— South Korea
- Korea College of Cosmetic Surgery
- ACP— USA
- American College of Prosthodontists
- CFCP— France
- French College of Plastic Surgery
- AMB— Brazil
- Associação Médica Brasileira
- SCCPFR— Colombia
- Sociedad Colombiana de Cirugía Plástica Facial y Rinología
- ARS— USA
- American Rhinologic Society
- CSFPS— USA
- California Society of Facial Plastic Surgery
- AMA— USA
- American Medical Association
- AAO-HNS— USA
- American Academy of Otolaryngology—Head and Neck Surgery
- AAO-HNSF— USA
- American Academy of Otolaryngology Foundation
- AHNS— USA
- American Head and Neck Society
- ASBS— USA
- American Society of Breast Surgeons
- FSPS— USA
- Florida Society of Plastic Surgeons
- CSPS— USA
- California Society of Plastic Surgeons
- NYFPSS— USA
- New York Facial Plastic Surgery Society
- NVEPC— Netherlands
- Nederlandse Vereniging voor Esthetische Plastische Chirurgie
- AOA— USA
- Alpha Omega Alpha Medical Honor Society
- TMA— USA
- Texas Medical Association
- MRCS— UK
- Member of the Royal College of Surgeons
- AWS— USA
- Association of Women Surgeons
- PTChPRiE— Poland
- Polskie Towarzystwo Chirurgii Plastycznej, Rekonstrukcyjnej i Estetycznej (Polish Society of Plastic, Reconstructive and Aesthetic Surgery)
- RSPS— Russia
- Russian Society of Plastic Surgeons
- SECPRF— Spain
- Sociedad Española de Cirugía Plástica Facial
- AAE— USA
- American Association of Endodontists
- OCMA— USA
- Orange County Medical Association
- ACOMS— Asia-Pacific
- Asian Congress of Oral & Maxillofacial Surgery
Fellow Titles (Post-Nominal) (24)
Honorific designations awarded by colleges or societies, typically shown after a surgeon's name (e.g. "Dr. Jane Doe, FACS"). Most fellow titles are conferred after admission to a senior tier of the parent body.
- FACS— USA
- Fellow of the American College of Surgeons
- FAAFPRS— USA
- Fellow of the American Academy of Facial Plastic and Reconstructive Surgery
- FRCS— UK
- Fellow of the Royal College of Surgeons
- FRCS-Ed— UK
- Fellow of the Royal College of Surgeons of Edinburgh
- FRCS-Glasg— UK
- Fellow of the Royal College of Physicians and Surgeons of Glasgow
- FRCSC— Canada
- Fellow of the Royal College of Physicians and Surgeons of Canada
- FRACS— Australia / NZ
- Fellow of the Royal Australasian College of Surgeons
- FRCSI— Ireland
- Fellow of the Royal College of Surgeons in Ireland
- FEBOPRAS— Europe
- Fellow of the European Board of Plastic, Reconstructive and Aesthetic Surgery
- FEBO— Europe
- Fellow of the European Board of Ophthalmology
- FICS— International
- Fellow of the International College of Surgeons
- FAACS— USA
- Fellow of the American Academy of Cosmetic Surgery
- FAAD— USA
- Fellow of the American Academy of Dermatology
- FACMS— USA
- Fellow of the American College of Mohs Surgery
- FEBORL-HNS— Europe
- Fellow of the European Board of Otorhinolaryngology – Head and Neck Surgery
- FCPS-Pakistan— Pakistan
- Fellow of the College of Physicians and Surgeons Pakistan
- FFDRCSI— Ireland
- Fellow of the Faculty of Dentistry, Royal College of Surgeons in Ireland
- FRCP— UK
- Fellow of the Royal College of Physicians
- FADSA— USA
- Fellow of the American Dental Society of Anesthesiology
- MRCGP— UK
- Member of the Royal College of General Practitioners
- FAMS— Singapore
- Fellow of the Academy of Medicine, Singapore
- MRCS-Ed— UK
- Member of the Royal College of Surgeons of Edinburgh
- FEBOMS— Europe
- Fellow of the European Board of Oral and Maxillofacial Surgery
- FPAPRAS— Philippines
- Fellow of the Philippine Association of Plastic, Reconstructive and Aesthetic Surgeons
Frequently Asked Questions
What is the SMAS in a facelift?
What is a rhytidectomy?
What are retaining ligaments and why do they matter?
What is the difference between a deep plane and a superficial plane facelift?
What is a hematoma after facelift and how is it treated?
What does the platysma do and why is it addressed in a facelift?
What is the cervicomental angle and why does it matter?
What does 'extended deep plane' mean exactly?
What is 'SMASectomy' and how is it different from deep plane?
What is the 'prezygomatic space' and why does it matter for deep plane technique?
What does SMAS stand for in deep plane facelift surgery?
SMAS stands for Superficial Musculoaponeurotic System — a fibromuscular layer connecting facial muscles to the overlying skin. In a deep plane facelift, the surgeon dissects beneath this layer to release the retaining ligaments (zygomatic, masseteric, and mandibular) and reposition the deep facial fat compartments. This sub-SMAS dissection is what distinguishes the deep plane technique from a standard SMAS facelift and contributes to its longer-lasting, more natural results. (DEEPPLANE™ Glossary, 2026.)
Scientific References
- 01Hamra ST. The deep-plane rhytidectomy. Plast Reconstr Surg. 1990;86(1):53-61(új lapon nyílik meg)(Folyóiratcikk)Hozzáférve: 2026-03-21DOI: 10.1097/00006534-199007000-00008
- 02American Society of Plastic Surgeons - Facelift Statistics 2024(új lapon nyílik meg)(Szervezet)Hozzáférve: 2026-03-21
- 03Owsley JQ. Face lifting: problems, solutions, and an outcome study. Plast Reconstr Surg. 2000;105(1):302-313(új lapon nyílik meg)(Folyóiratcikk)Hozzáférve: 2026-08-05
Hivatkozás erre az oldalraCC-BY 4.0
DEEPPLANE™ Szerkesztőbizottság (2026). Deep Plane Facelift Glossary: 40+ Medical Terms Explained. DEEPPLANE™. Forrás: https://deepplane.com/glossary
DEEPPLANE™. Deep Plane Facelift Glossary: 40+ Medical Terms Explained. deepplane.com. Frissítve: 2026-09-30. https://deepplane.com/glossary
DEEPPLANE™ Szerkesztőbizottság. "Deep Plane Facelift Glossary: 40+ Medical Terms Explained." DEEPPLANE™. Utolsó módosítás: 2026-09-30. https://deepplane.com/glossary.
DEEPPLANE™ Szerkesztőbizottság. "Deep Plane Facelift Glossary: 40+ Medical Terms Explained." DEEPPLANE™, 2026-09-30, https://deepplane.com/glossary.
@misc{deepplane_https_deepplane_com_glossary,
  author = {DEEPPLANE™ Szerkesztőbizottság},
  title  = {Deep Plane Facelift Glossary: 40+ Medical Terms Explained},
  year   = {2026},
  url    = {https://deepplane.com/glossary},
  note   = {Last modified 2026-09-30. Licensed CC-BY 4.0.},
}
<a href="https://deepplane.com/glossary">Deep Plane Facelift Glossary: 40+ Medical Terms Explained — DEEPPLANE™</a>
Tartalom licencelve CC-BY 4.0. Szabadon megosztható a DEEPPLANE™ feltüntetésével.